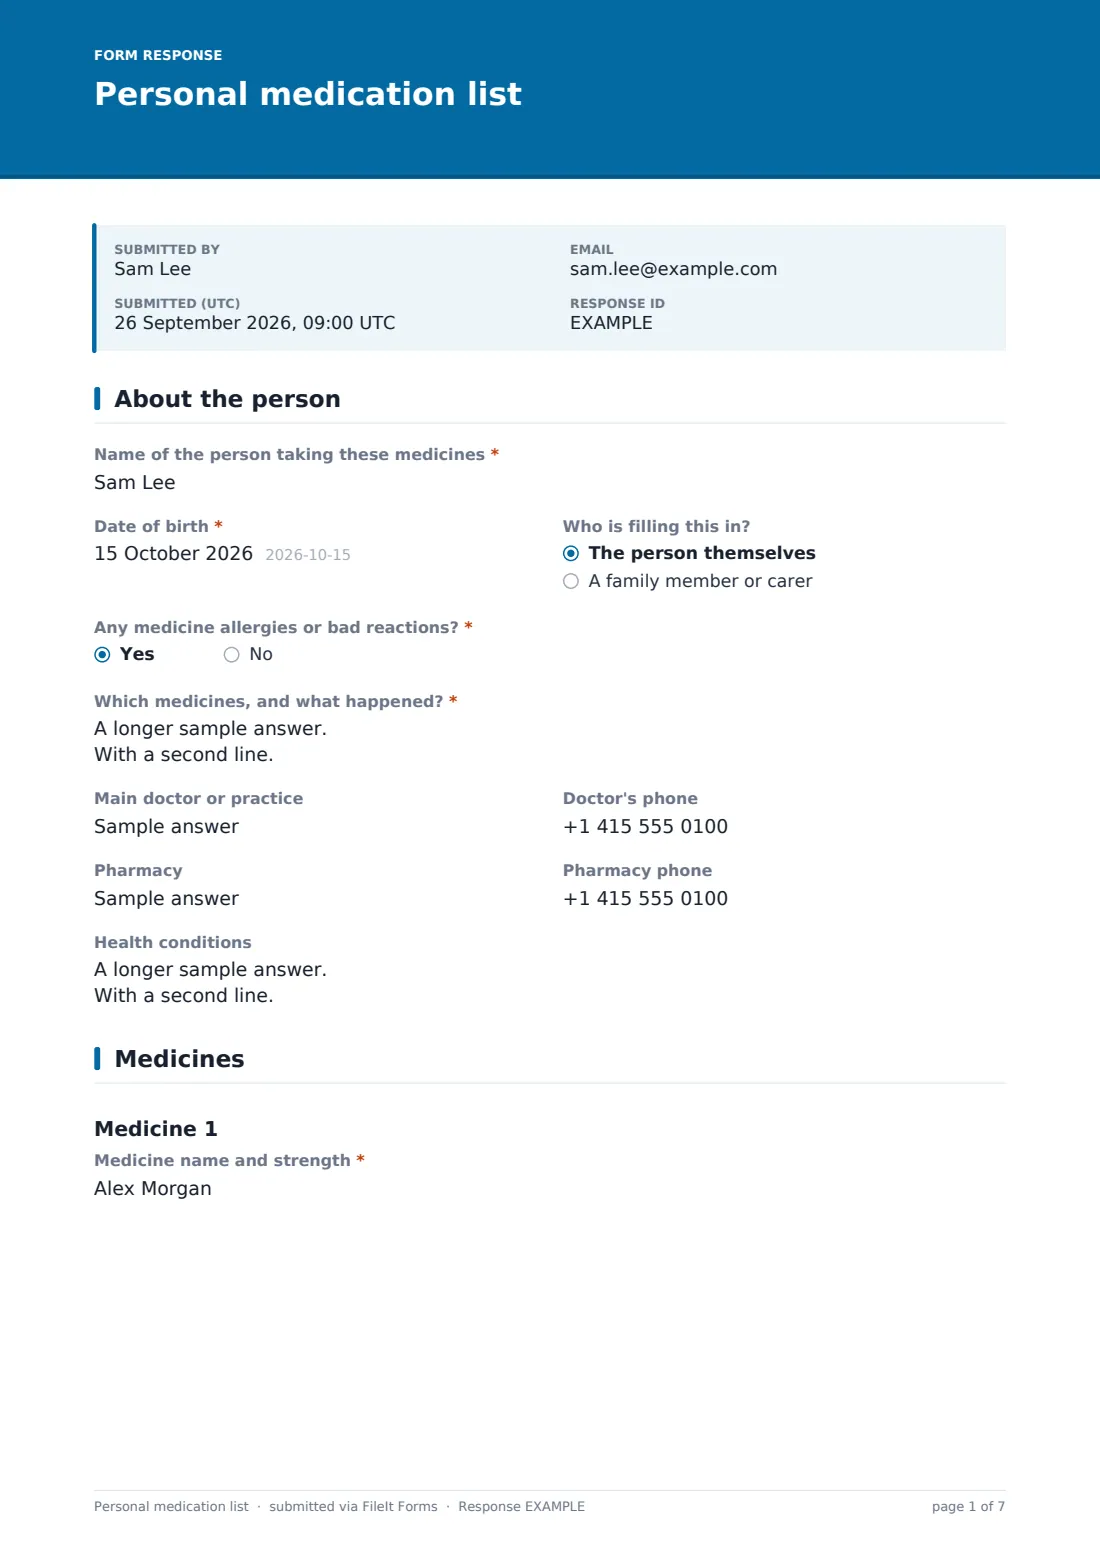






What is the personal medication list form template?
"What medicines are you on?" is one of the first questions at any appointment, and one of the hardest to answer accurately from memory. Strengths get muddled, the once-a-week tablet gets forgotten, and the supplements never get mentioned at all. For someone who sees several specialists, or a carer managing a parent's medicines, a written list is the simplest safeguard there is.
This template starts with the essentials: the person's name and date of birth, any medicine allergies, the main doctor, the pharmacy and current health conditions. Then each medicine gets the same short section, with "Medicine name and strength", "Dose", "How often", "When, or how to take it", "What it's for", "Prescribed by" and "Start date". Answering "Add another medicine?" opens the next, up to eight, with a box for any more.
The last page collects what usually gets left off: over-the-counter medicines, supplements, recently stopped medicines and photos of the labels. Each version is saved as a dated PDF in your FileIt vault, filed under the family member it belongs to.
- Best for
- Patients on several medicines, carers, and families managing an older relative's care
- Filled in by
- The patient, or a family member or carer
- Time to complete
- 10–15 minutes the first time
- Includes
- Up to eight medicines with a repeating section, allergies, supplements, label photos
Who uses a personal medication list form?
- Taking a current list to a new specialist or a hospital admission
- An adult child keeping track of a parent's prescriptions
- Preparing for a medication review with a pharmacist
- Keeping a child's list ready for school, camp or a babysitter
- Having a copy in the vault for travel or an emergency
Questions on this personal medication list form
81 questions over 3 pages · includes file upload, conditional questions, multiple pages.
1 About the person
- Name of the person taking these medicines*
- Date of birth*
- Who is filling this in? The person themselves · A family member or carer
- Your name and relationship asked only when it applies
- Any medicine allergies or bad reactions?*
- Which medicines, and what happened?* asked only when it applies
- Main doctor or practice
- Doctor's phone
- Pharmacy
- Pharmacy phone
- Health conditions
2 Medicines
- Medicine name and strength*
- Dose*
- How often* Once a day · Twice a day · Three times a day · Four times a day · Every other day · Once a week · Once a month · Only when needed · Other
- When, or how to take it
- What it's for
- Prescribed by
- Start date
- Add another medicine?*
- Medicine name and strength* asked only when it applies
- Dose* asked only when it applies
- How often* asked only when it applies Once a day · Twice a day · Three times a day · Four times a day · Every other day · Once a week · Once a month · Only when needed · Other
- When, or how to take it asked only when it applies
- What it's for asked only when it applies
- Prescribed by asked only when it applies
- Start date asked only when it applies
- Add another medicine?* asked only when it applies
- Medicine name and strength* asked only when it applies
- Dose* asked only when it applies
- How often* asked only when it applies Once a day · Twice a day · Three times a day · Four times a day · Every other day · Once a week · Once a month · Only when needed · Other
- When, or how to take it asked only when it applies
- What it's for asked only when it applies
- Prescribed by asked only when it applies
- Start date asked only when it applies
- Any other medicines asked only when it applies
3 Other medicines & checks
- Over-the-counter medicines taken regularly
- Vitamins, supplements and herbal remedies
- Medicines stopped recently, and why
- Recent vaccinations
- Photos of labels or the pharmacy list
- Date this list was checked*
The personal medication list form, page by page
1 About the person
"Name of the person taking these medicines" and "Date of birth" are required. "Who is filling this in?" separates the person from a family member or carer, and a carer adds their name and relationship. "Any medicine allergies or bad reactions?" is required, and a yes asks which medicines and what happened. The doctor's and pharmacy's names and phone numbers and "Health conditions" are optional.
2 Medicines
Each medicine has its own heading. The name and strength, "Dose" and "How often" are required. The frequency options run from once a day to once a month, plus "Only when needed" and Other. When to take it, what it's for, who prescribed it and the start date are optional. A required "Add another medicine?" after each one opens the next, up to eight, and "Any other medicines" takes the rest.
3 Other medicines & checks
Optional boxes cover over-the-counter medicines, "Vitamins, supplements and herbal remedies", "Medicines stopped recently, and why" and recent vaccinations. Up to ten photos of labels or the pharmacy's printed list can be uploaded. The required "Date this list was checked" closes the form, under a reminder that the list doesn't replace instructions from a doctor or pharmacist.
Make the template yours
- Set the form's person in Settings so each list is filed under that family member in your vault
- Add a "Prescription number" field to each medicine if you order refills yourself
- Add more medicine sections in the designer if eight isn't enough
- Remove the vaccinations question, or swap it for one your clinic needs
- Change the frequency options to the times your household uses, such as morning, noon and night
- Share the form with a sibling who also helps with a parent's care
Tips for a better personal medication list form
- Copy names and strengths from the box or the pharmacy label, not from memory
- Include creams, inhalers, eye drops and injections. They're medicines too
- Submit a fresh list whenever a medicine is started, stopped or changed
- Upload a photo of each box. It settles questions about spelling and strength
- Keep a printed copy in a wallet or bag for emergencies
Every response becomes a PDF in your vault
Each list becomes a PDF titled with the person's name and the date, filed in the vault folder you chose, with any label photos attached. You can get a copy by email to print or show at an appointment.
Because every version is kept, you can open the Responses table to see when a medicine was added or dropped. That's useful when a doctor asks when something changed.
- Start from this template. It opens in the FileIt Forms designer — change any question, add pages, set the rules for when questions appear.
- Share it. Turn on a public link, or send it to people by email, each with their own link. They don’t need a FileIt account.
- Get the answers as PDFs. Each response is saved as a PDF in the vault folder you choose, with uploaded files attached — and listed in a Responses table you can export to CSV.
Personal medication list form: frequently asked questions
How many medicines can I list?
Eight in full, each with its own section, plus an "Any other medicines" box. You can add more sections in the designer.
Can a carer fill it in for someone else?
Yes. Choose "A family member or carer" under "Who is filling this in?" and add your name and relationship.
Will FileIt check for drug interactions?
No. FileIt stores the list but doesn't review medicines or give medical advice. Ask your pharmacist or doctor to review it.
Can I file it under a family member?
Yes. Set the person in the form's settings and every response is filed under them in your vault.
Is this template free?
Yes. It's one of the starter templates in FileIt Forms, available on every plan.