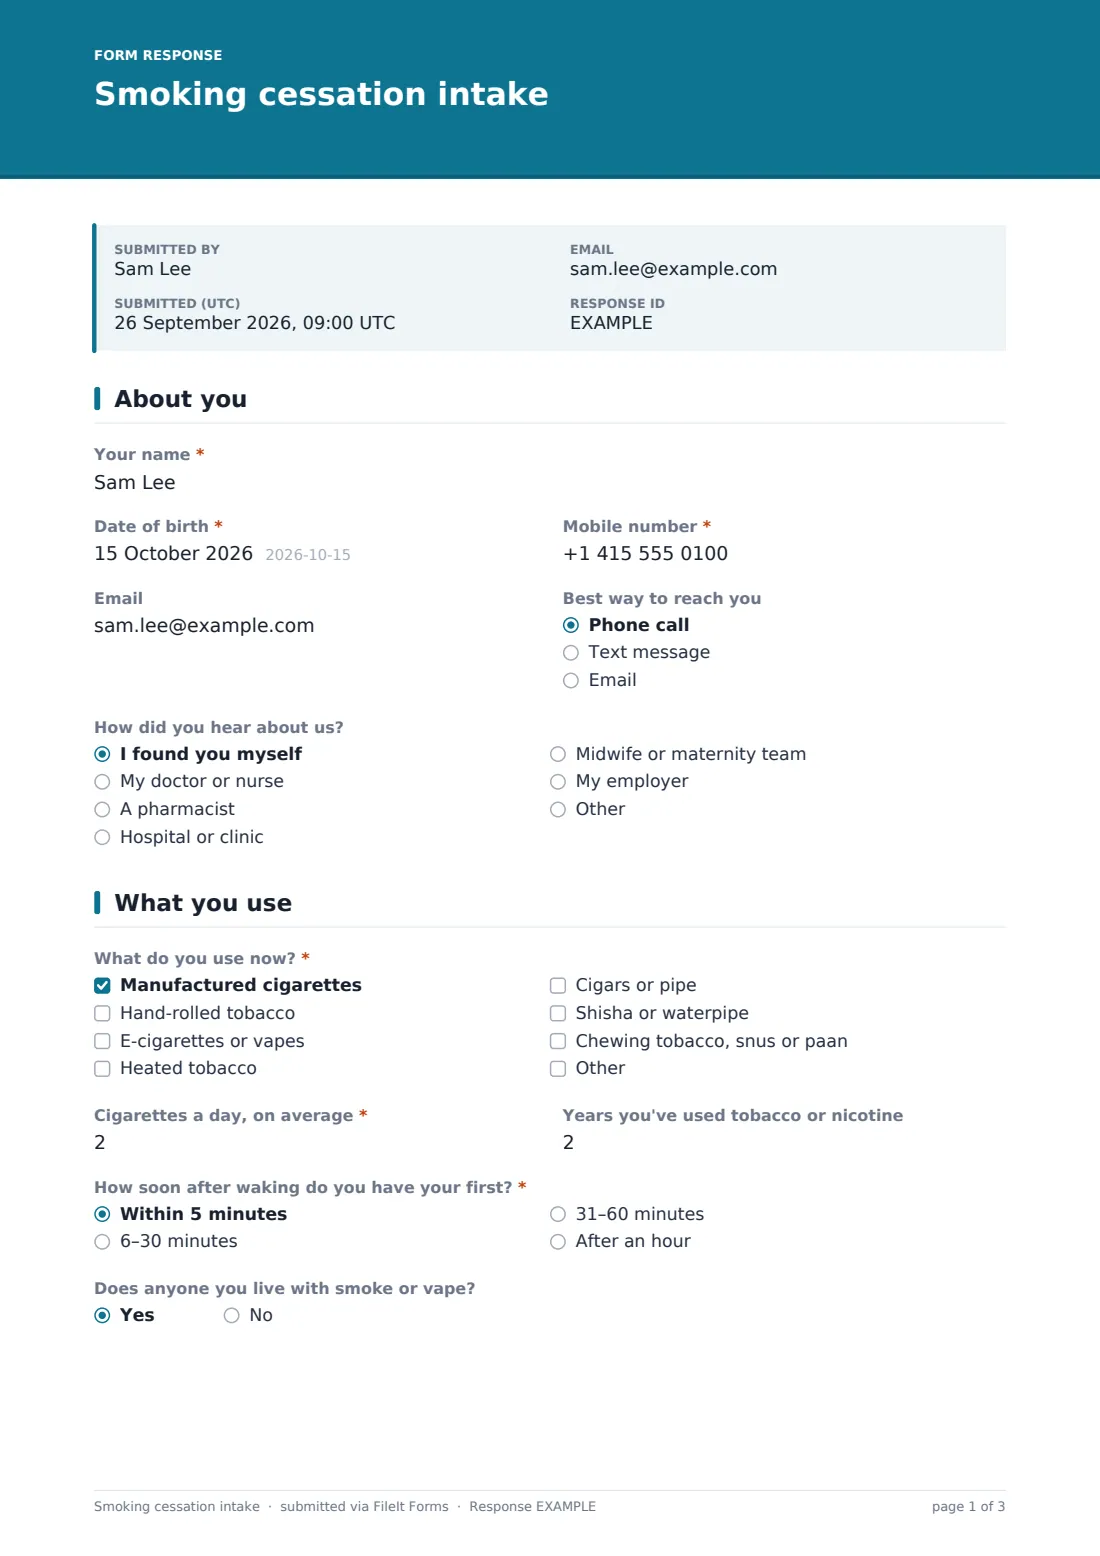


What is the smoking cessation intake form template?
Helping someone stop smoking starts with understanding how they use tobacco or nicotine now, what's worked or not worked before, and what's likely to trip them up. Advisors usually gather this in the first session; collecting it beforehand frees that session for planning the quit itself.
This template asks the client what they use — cigarettes, hand-rolled tobacco, vapes, heated tobacco, cigars, shisha or chewing tobacco — with follow-ups for how much, how long they've used it and how soon after waking they have their first. It then covers past quit attempts and methods, what helped and what led them back, the moments they most want to smoke, their reasons for quitting, how motivated and confident they feel, and a quit date if they have one in mind.
The last page records pregnancy or breastfeeding, health conditions and medicines that an advisor or prescriber will want to know about, allergies, how the client wants to be supported, and whether they're interested in nicotine replacement or medication. Each intake is filed as a PDF in FileIt.
- Best for
- Stop-smoking services, pharmacies, GP practices, workplace health and maternity teams
- Filled in by
- The person who wants to quit
- Time to complete
- About 6 minutes
- Includes
- Product-specific follow-ups, past attempts, triggers, motivation and confidence scales, health conditions, support preferences and consent
Who uses a smoking cessation intake form?
- A community stop-smoking service taking self-referrals online
- A pharmacy offering a quit programme
- A GP practice referring patients to a smoking advisor
- Maternity teams supporting pregnant smokers
- Workplace health schemes offering quit support
- Pre-surgery clinics encouraging patients to stop before an operation
Questions on this smoking cessation intake form
29 questions over 4 pages · includes conditional questions, multiple pages, consent checkbox, ratings.
1 About you
- Your name*
- Date of birth*
- Mobile number*
- Best way to reach you Phone call · Text message · Email
- How did you hear about us? I found you myself · My doctor or nurse · A pharmacist · Hospital or clinic · Midwife or maternity team · My employer
2 What you use
- What do you use now?* Manufactured cigarettes · Hand-rolled tobacco · E-cigarettes or vapes · Heated tobacco · Cigars or pipe · Shisha or waterpipe · Chewing tobacco, snus or paan
- Cigarettes a day, on average* asked only when it applies
- Hand-rolled tobacco a week asked only when it applies
- Vape type, nicotine strength and how much you use asked only when it applies
- Years you've used tobacco or nicotine
- How soon after waking do you have your first?* Within 5 minutes · 6–30 minutes · 31–60 minutes · After an hour
- Does anyone you live with smoke or vape?
3 Quitting
- Serious quit attempts before
- Longest time you stayed stopped
- What have you tried before? Willpower alone · Nicotine patches · Gum, lozenges, spray or inhalator · Prescribed stop-smoking medication · Switching to a vape · Counselling or a support group · An app or website
- What helped, and what made you start again?
- When do you most want to smoke or vape? First thing in the morning · When stressed or upset · After meals · With alcohol or coffee · Driving · Breaks at work · When bored · With friends who smoke
- Your reasons for quitting* My health · Saving money · My family or children · Pregnancy or planning a baby · Advice from a health professional · Fitness · Upcoming surgery
- How much do you want to quit?*
- How confident are you that you can quit?*
- Quit date you'd like to aim for
4 Health & support
- Are you pregnant or breastfeeding?* Pregnant · Breastfeeding · No · Not applicable
- Health conditions* Heart disease or recent heart attack · High blood pressure · Stroke · Asthma, COPD or other lung condition · Diabetes · Epilepsy or seizures · Depression, anxiety or other mental health condition · Kidney or liver problems · None of these
- Medicines you take
- Allergies, including to plasters or adhesives
- How would you like support?* One-to-one in person · Phone calls · Video calls · Group sessions · Text or app reminders
- Interested in nicotine replacement or stop-smoking medication?* Yes · I'd like to talk about it · No
- Consent*
The smoking cessation intake form, page by page
1 About you
The client gives their name, date of birth, mobile number, email and the best way to reach them, and says how they heard about the service — on their own, through a doctor, pharmacist, hospital, midwife or employer.
2 What you use
The client ticks everything they use now. Cigarettes ask how many a day, hand-rolled tobacco asks how much a week, and vapes ask for the device, nicotine strength and how much. They then give how many years they've used tobacco or nicotine, how soon after waking they have their first, and whether anyone they live with smokes or vapes.
3 Quitting
This page covers past serious quit attempts, the longest time they stayed stopped and the methods tried, from willpower and patches to prescribed medication, vapes, counselling and apps, plus what helped and what made them start again. The client ticks their triggers and reasons for quitting, rates how much they want to quit and how confident they feel on 1–10 scales, and can suggest a quit date.
4 Health & support
The client says whether they're pregnant or breastfeeding, ticks health conditions such as heart disease, lung conditions, diabetes, seizures or mental health conditions, and lists medicines and allergies. They choose how they'd like support — in person, phone, video, group or text reminders — say whether they're interested in nicotine replacement or medication, and agree to the service keeping their information.
Make the template yours
- Add your service's opening hours and what happens next to the cover text
- Add a question about carbon monoxide testing if you offer it at the first visit
- Change the support options to the ones your service provides
- Prefill the referring practice with personal links for each referrer
- Route maternity referrals to a separate vault folder
- Add your local privacy notice to the consent statement
Tips for a better smoking cessation intake form
- Call new clients soon after they submit — motivation can fade quickly
- Use the triggers list to plan coping strategies in the first session
- Review health conditions and medicines before recommending any product
- Remember quitting can change how some medicines work; check with a pharmacist
- Treat past relapses as learning, not failure
- Agree a quit date together if the client left it blank
Every response becomes a PDF in your vault
Each intake is saved as a PDF in the vault folder you choose, and the account owner can be emailed when a new one arrives, so an advisor can call the client promptly.
In Responses, filter by date or referral source, or export to CSV to see how clients found you and which support options they prefer.
- Start from this template. It opens in the FileIt Forms designer — change any question, add pages, set the rules for when questions appear.
- Share it. Turn on a public link, or send it to people by email, each with their own link. They don’t need a FileIt account.
- Get the answers as PDFs. Each response is saved as a PDF in the vault folder you choose, with uploaded files attached — and listed in a Responses table you can export to CSV.
Smoking cessation intake form: frequently asked questions
Is this smoking cessation intake template free?
Yes. It's part of the Forms app, included with every FileIt account, the free plan too.
Does this form cover vaping too?
Yes. Vapes are one of the products clients can tick, with a follow-up for the device, nicotine strength and how much they use.
Does the form recommend a treatment?
No. It collects information for an advisor or prescriber, who decides with the client what support and products are suitable.
Is the 'first thing in the morning' question a dependence score?
It asks how soon after waking the client has their first cigarette or vape, which advisors often use as one indicator of dependence. The form doesn't calculate a score.
Can clients fill it in on their phone?
Yes. It works in any phone browser and doesn't need an account.
Who can see the answers?
Responses are filed in your FileIt vault. Keep them in a folder only your advisors can open.