
What is the disability insurance claim form template?
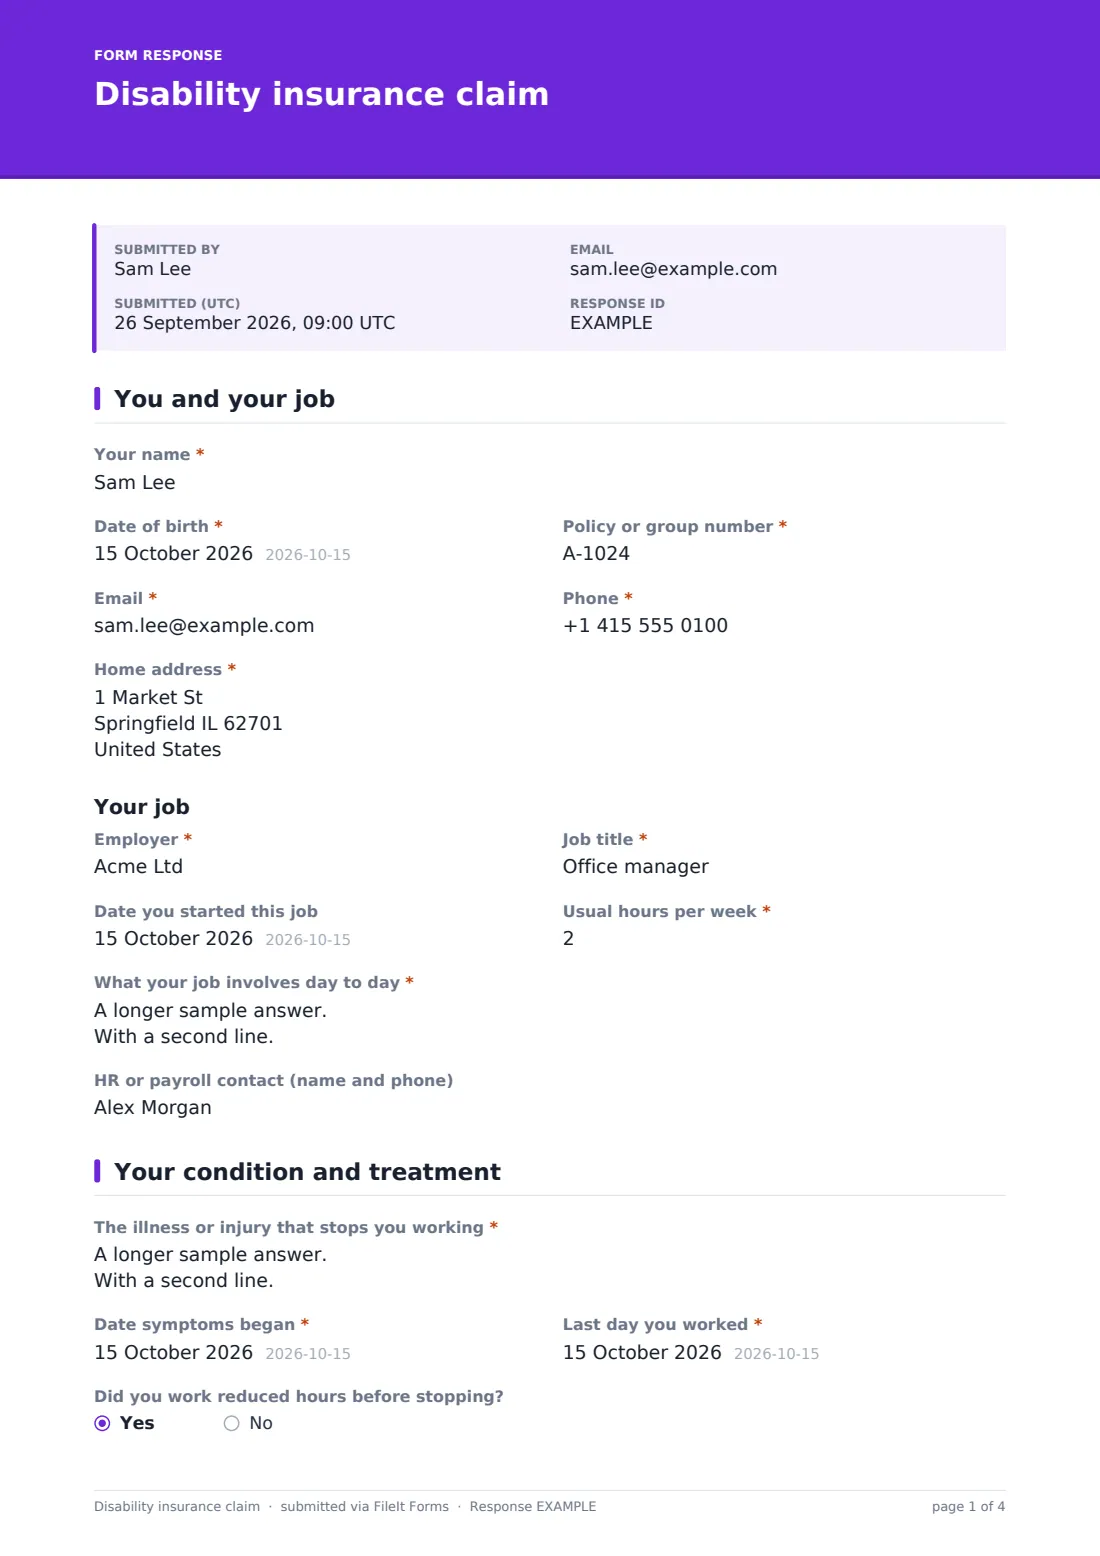
When someone can't work because of illness or injury, a disability claim is one more thing to do on a hard day. The claim needs a lot: what the job involves, when the symptoms began, the last day worked, who's treating them and what they earned. This disability insurance claim form template splits it into three short pages, so it's manageable and a claimant can take breaks.
It suits insurers, brokers, benefits administrators and HR teams helping staff with group short-term or long-term disability claims. The first page covers the claimant and the job they can no longer do. The second covers the condition, treatment and the treating physician. Answering yes to Is your condition related to your work? opens a workers' compensation section: whether a claim has been filed, the insurer and claim number, where that claim stands, and the weekly amount being received.
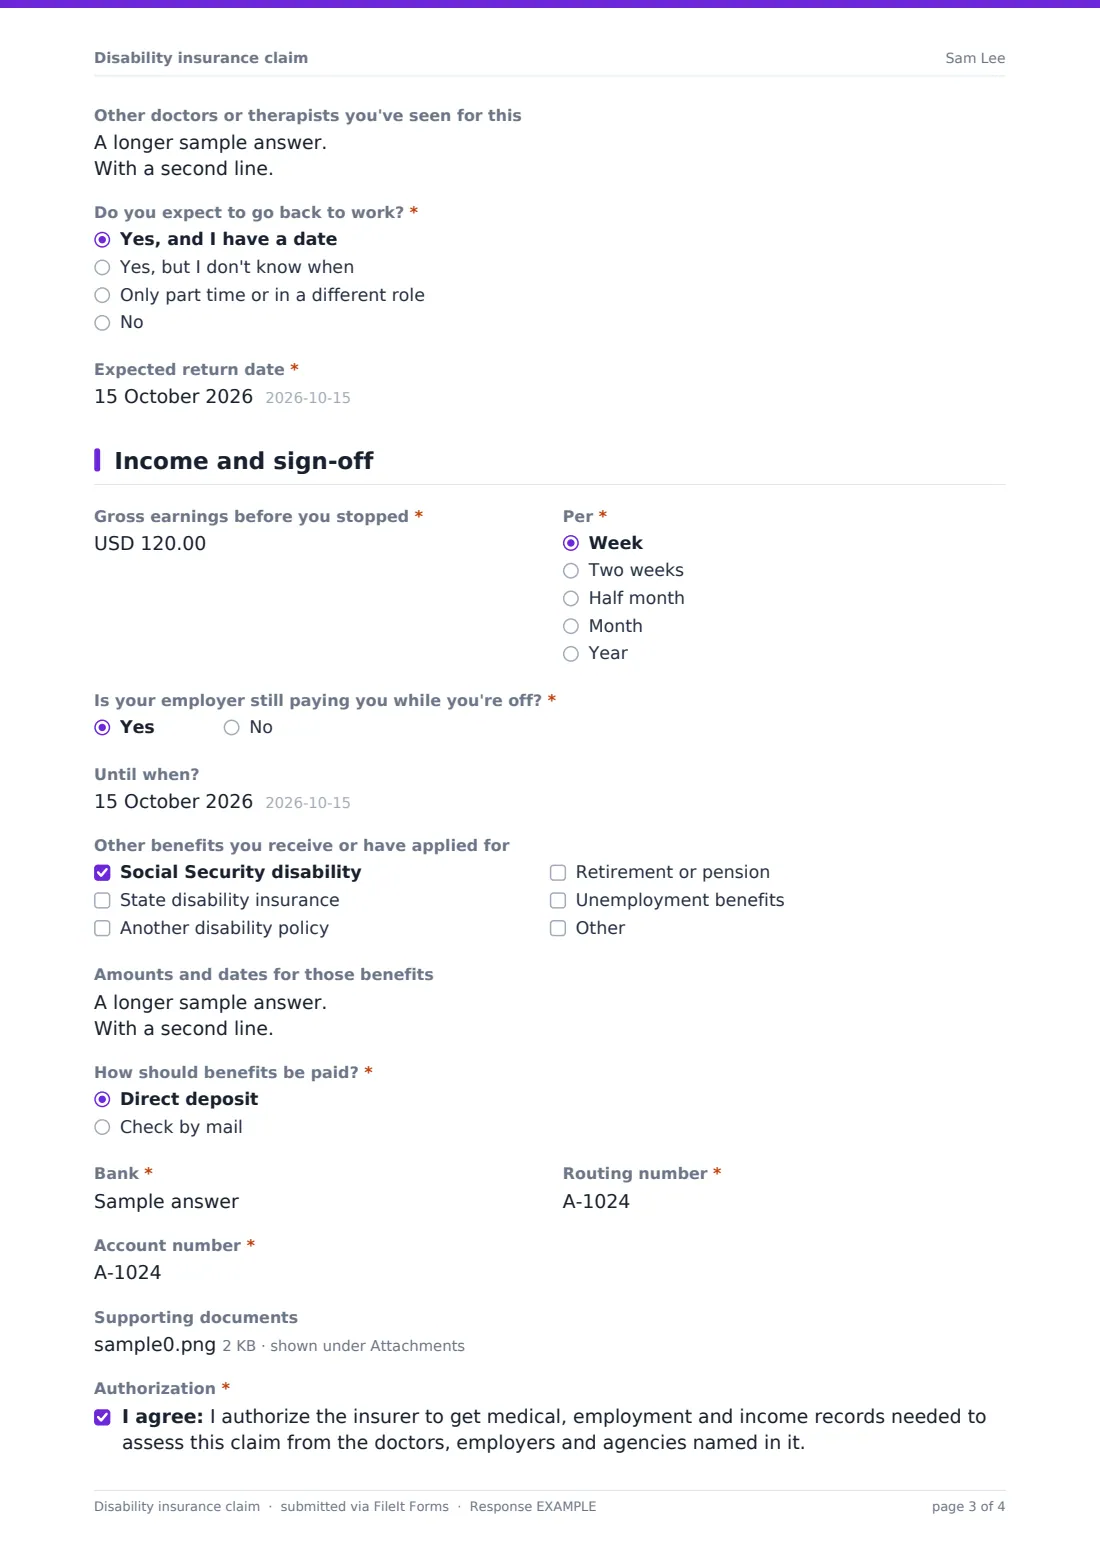
The third page covers income, other benefits and how payments should be made, followed by an authorization, a declaration and a signature. Each claim is saved as a PDF in your FileIt vault with supporting documents attached.
- Best for
- Disability insurers, brokers, benefits administrators and HR teams
- Filled in by
- The claimant, or a family member helping them
- Time to complete
- About 15 minutes
- Includes
- Job duties, condition and dates, accident and workers' compensation logic, physician details, income, payment details, signature
Who uses a disability insurance claim form?
- An HR team helping an employee start a group short-term disability claim
- A broker collecting a client's claimant statement for an income protection policy
- A benefits administrator replacing a long paper claim packet
- A claimant whose condition is work-related and who also has a workers' compensation claim
- Claims after an accident outside work, such as a car crash or a fall
- Collecting the claimant's part before the physician completes their own statement
Questions on this disability insurance claim form
53 questions over 3 pages · includes signature, file upload, conditional questions, multiple pages, consent checkbox.
1 You and your job
- Your name*
- Date of birth*
- Policy or group number*
- Email*
- Phone*
- Home address*
- Employer*
- Job title*
- Date you started this job
- Usual hours per week*
- What your job involves day to day*
- HR or payroll contact (name and phone)
2 Your condition and treatment
- The illness or injury that stops you working*
- Date symptoms began*
- Last day you worked*
- Did you work reduced hours before stopping?
- From when, and how many hours a week? asked only when it applies
- Was it caused by an accident?*
- Where and when did it happen, and how?* asked only when it applies
- Is your condition related to your work?*
- Have you filed a workers' compensation claim?* asked only when it applies
- Workers' compensation insurer asked only when it applies
- Claim number asked only when it applies
- Where does that claim stand?* asked only when it applies Still being decided · Approved · Denied · Settled
- Weekly amount you receive from it asked only when it applies
- Have you been admitted to a hospital for this?
- Hospital and dates asked only when it applies
- Physician's name*
- Specialty
- Practice phone*
- First visit for this condition*
- Most recent visit
- Next appointment
- Practice address
- Treatment so far
- Other doctors or therapists you've seen for this
- Do you expect to go back to work?* Yes, and I have a date · Yes, but I don't know when · Only part time or in a different role · No
- Expected return date* asked only when it applies
3 Income and sign-off
- Gross earnings before you stopped*
- Per* Week · Two weeks · Half month · Month · Year
- Is your employer still paying you while you're off?*
- Until when? asked only when it applies
- Other benefits you receive or have applied for Social Security disability · State disability insurance · Another disability policy · Retirement or pension · Unemployment benefits
- Amounts and dates for those benefits
- How should benefits be paid?* Direct deposit · Check by mail
- Bank* asked only when it applies
- Routing number* asked only when it applies
- Account number* asked only when it applies
- Supporting documents
- Authorization*
- Declaration*
- Signature*
- Date*
The disability insurance claim form, page by page
1 You and your job
The claimant gives their name, date of birth and policy or group number, then email, phone and home address. Under Your job, they enter the employer, job title, the date they started and usual hours per week. What your job involves day to day is required, with a prompt about lifting, standing, driving, computer work, travel and anything they can no longer do. An optional field takes an HR or payroll contact.
2 Your condition and treatment
The page asks about the illness or injury that stops the claimant working, the date symptoms began and the last day worked, all required. Did you work reduced hours before stopping? asks from when, and how many hours a week. Was it caused by an accident? is required and opens Where and when did it happen, and how?
Is your condition related to your work? is required too. A yes opens Workers' compensation: Have you filed a workers' compensation claim?, and if so the insurer, the claim number, where that claim stands (still being decided, approved, denied or settled), and the weekly amount received from it. A hospital admission question asks for the hospital and dates.
Under Treating physician, the claimant gives the physician's name, specialty, practice phone, practice address and the dates of the first visit for this condition, the most recent visit and the next appointment. Treatment so far and other doctors or therapists seen are free-text. Do you expect to go back to work? offers a date, an unknown date, part time or a different role, or no. Choosing a date asks for the expected return date.
3 Income and sign-off
The claimant enters gross earnings before they stopped and the pay period. Is your employer still paying you while you're off? asks until when. Other benefits you receive or have applied for lists Social Security disability, state disability insurance, another disability policy, retirement or pension and unemployment benefits, with a box for amounts and dates.
How should benefits be paid? offers direct deposit, which asks for the bank, routing number and account number, or a check by mail. Supporting documents such as a doctor's note can be uploaded. The claimant agrees to an authorization for records and a declaration, then signs and dates the claim.
Make the template yours
- Rewrite the authorization in your own insurer's approved wording
- Add a separate form for the attending physician's statement and the employer's statement
- Change the other benefits list for claimants outside the US
- Add an elimination period or policy type question if your products vary
- Remove the payment section if benefits are always paid through payroll
- Restrict the vault folder where claims are filed, since they contain health and bank details
Tips for a better disability insurance claim form
- Describe the job in practical terms, like how long you stand, what you lift, how much you drive
- Use the dates from your doctor's notes so everything lines up
- List every benefit you've applied for, even if it hasn't been decided yet
- Keep a copy of the claim, and tell the insurer as soon as anything changes
Every response becomes a PDF in your vault
The signed claim is saved as a PDF in the vault folder you choose, titled with the claimant's name, with supporting documents attached. Your claims team is notified by email, and the claimant can get their own copy.
In the Responses table, claims handlers can see every new claim, open it to review, and export to CSV for a list of claimants, dates off work and workers' compensation status.
- Start from this template. It opens in the FileIt Forms designer — change any question, add pages, set the rules for when questions appear.
- Share it. Turn on a public link, or send it to people by email, each with their own link. They don’t need a FileIt account.
- Get the answers as PDFs. Each response is saved as a PDF in the vault folder you choose, with uploaded files attached — and listed in a Responses table you can export to CSV.
Disability insurance claim form: frequently asked questions
Is this disability claim template free?
Yes. It's a starter template in FileIt's Forms app, on every plan including free.
When do the workers' compensation questions appear?
Only when the claimant answers yes to Is your condition related to your work? They then cover the filing, the insurer, the claim number, its status and any weekly amount.
Does the form decide whether the claim is paid?
No. It gathers the claimant's statement and documents. Decisions depend on the policy and are made by the insurer.
Does the doctor fill in this form too?
No. It's the claimant's part. Many insurers also need a statement from the treating physician, which you can build as a separate form.
Is this legal or medical advice?
No. It's a way to collect a claim clearly. For questions about your rights or your health, speak to a qualified professional.
Does the claimant need a FileIt account?
No. They fill it in from a link or an email request and sign on screen without signing up.